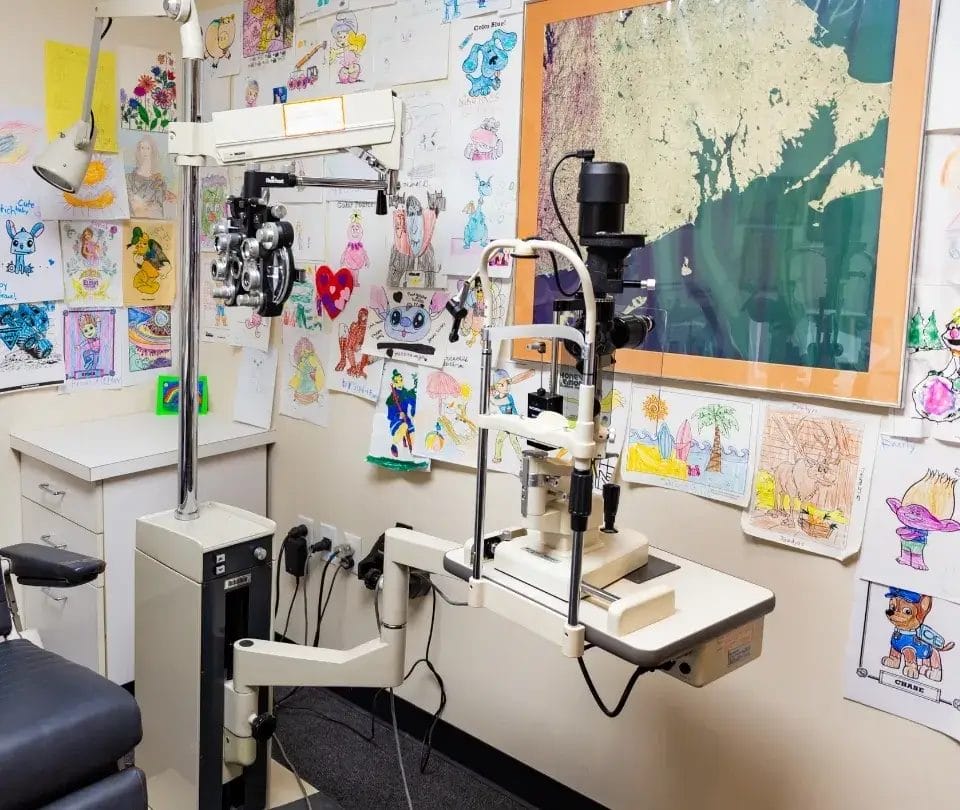
Children’s Vision Care
How Your Child's Vision Develops
Children's eyes change dramatically from birth through late adolescence. Understanding what is normal at each stage helps you notice when something may need attention.
Newborns can only see objects about 8 to 12 inches away, roughly the distance to a parent's face during feeding. Over the first few months, babies learn to track moving objects, recognize faces, and begin to perceive color. By six months, most infants have developed basic depth perception and improved eye coordination.
Around their first birthday, babies typically can recognize people and objects across a room. Their eye-hand coordination grows steadily, allowing them to reach for toys with more accuracy. If your baby's eyes appear consistently misaligned beyond three to four months, schedule an evaluation promptly.
Between ages one and three, toddlers refine their visual skills quickly as they explore their environment. Depth perception improves, helping them navigate stairs, judge distances, and coordinate their hands and eyes during play.
Preschoolers between three and five sharpen their vision in preparation for reading and writing. They begin recognizing shapes, letters, and numbers, all of which require precise eye movements and focus. This period is especially important for detecting vision problems before they interfere with school readiness.
Elementary school children use their vision intensively for reading, writing, and screen-based learning. Their eyes must shift focus between the board, their desks, and digital devices throughout the day. Many refractive errors, including nearsightedness, first appear during these years.
As academic demands grow, so does the strain on young eyes. Regular eye exams during this period help ensure that vision keeps pace with learning. Early detection and correction of vision problems can prevent struggles with reading, attention, and self-confidence.
Nearsightedness often progresses during adolescence as the eyes continue to grow. Increased academic workload, heavy screen use, and reduced outdoor time can all contribute to vision changes. Many teenagers need prescription updates more frequently than younger children.
By late adolescence, most eyes have reached their adult size and shape, though vision can still change into the early twenties. Monitoring vision throughout the teen years ensures that young people have the clear sight they need for driving, sports, and their future goals.
Common Vision Problems in Children
Several eye conditions appear commonly in childhood, and many respond well to treatment when caught early. Recognizing these conditions helps you take action before they affect your child's development or learning.
Myopia, or nearsightedness, occurs when the eyeball grows too long or the cornea is too steeply curved. This causes distant objects to appear blurry while close objects stay clear. Myopia often emerges between ages six and twelve and may worsen as children grow. Genetics, limited outdoor time, and extensive close-up work may all contribute.
- Squinting to see the board at school or distant objects
- Sitting very close to the television or holding books near the face
- Headaches or eye strain after visual tasks
- Difficulty with sports that require distance vision
Hyperopia, or farsightedness, occurs when the eyeball is shorter than normal. Many young children have mild farsightedness and naturally compensate without symptoms. However, moderate to high levels, or unequal amounts between the two eyes, can lead to eye crossing and lazy eye if not addressed.
Children with significant farsightedness may avoid reading, puzzles, or coloring, and may complain of headaches or eye discomfort after close work. Glasses help these children see comfortably while reducing the risk of related complications.
- Avoiding near activities like reading or coloring
- Headaches or eye discomfort after close work
- Eyes that turn inward, especially when tired
- Intermittent blurry vision or frequent eye rubbing
Astigmatism results from an irregular shape of the cornea or lens, causing blurred or distorted vision at all distances. Children with astigmatism may tilt their heads to see more clearly or describe objects as stretched or wavy. This condition often occurs alongside nearsightedness or farsightedness.
Most astigmatism in children is corrected with glasses or contact lenses. Early correction helps prevent eye strain and supports healthy visual development during critical learning years.
Amblyopia, commonly called lazy eye, develops when one eye has significantly poorer vision than the other. The brain begins relying on the stronger eye, and the weaker eye may never develop normal vision if the condition is left untreated. Common causes include eye misalignment, a significant difference in prescription between the two eyes, or anything that obstructs vision in early childhood.
Treatment is most effective when started early, though many children older than seven can still benefit. The first step is often full-time glasses to correct any refractive error. Additional treatments include patching the stronger eye to encourage use of the weaker one, atropine eye drops that temporarily blur the stronger eye, or addressing an underlying structural cause such as a cataract or drooping eyelid.
Strabismus is a misalignment of the eyes in which one or both eyes point in a different direction, whether inward, outward, upward, or downward. The condition may be constant or intermittent and can affect one eye or alternate between both.
- Eyes that do not move together or point in different directions
- Frequent squinting or closing one eye, especially in bright light
- Head tilting to use both eyes together
- Poor depth perception or unusual clumsiness
- Double vision in older children who can describe their symptoms
Color vision deficiency, often called color blindness, makes it difficult to distinguish between certain colors, most commonly reds and greens. This inherited condition is much more common in boys than girls, and severity varies. Most people with color vision deficiency retain functional color perception for everyday tasks, and while there is no cure, understanding the condition allows teachers and parents to make helpful accommodations.
We test for color vision deficiency during comprehensive eye exams, particularly when there is a family history. Knowing about the condition early helps you and your child's school provide the support they need to succeed.
Warning Signs Your Child May Have a Vision Problem
Children often cannot describe what they see, and many vision problems develop gradually without obvious complaints. Knowing what to look for helps you identify concerns before they affect learning and development.
Children with undetected vision problems often develop habits to compensate for their blurry sight. Watch for sitting very close to screens, holding books unusually near or far, or losing their place while reading. Frequent squinting, eye rubbing, or excessive blinking can also signal vision difficulties.
- Avoiding activities requiring distance vision, like ball games
- Avoiding books, puzzles, or detailed close work
- Very short attention span during visual tasks
- Covering or closing one eye to see better
Observable changes in your child's eyes or recurring physical complaints can indicate vision problems. Eyes that appear crossed, misaligned, or do not move together smoothly need evaluation. Drooping eyelids, pupils of unequal size, or unusual eye movements also warrant prompt attention.
Frequent headaches after reading or screen time, tired eyes, burning, or itching may point to vision issues or eye strain. Persistent redness, itching, or light sensitivity may suggest allergies or eyelid inflammation and should be evaluated. Any white, grayish, or unusual coloring in the pupil area requires immediate medical attention.
Vision problems can look a great deal like learning difficulties or behavioral issues. Children who cannot see the board clearly may appear inattentive or disruptive. Difficulty reading, poor handwriting, or trouble copying from the board can all stem from undetected vision problems.
Talk with your child's teachers and observe homework habits at home. If your child resists reading, shows frustration with schoolwork despite adequate ability, or makes frequent letter or number reversals beyond the expected age, a comprehensive eye exam is a worthwhile first step. Keep in mind that an eye exam addresses vision only, and broader learning concerns may also require educational or developmental evaluation.
Some symptoms require urgent attention and should not be waited out. Sudden vision loss, even if temporary, should never be ignored. Severe eye pain, persistent redness, discharge, or swelling need prompt evaluation to prevent complications.
If a chemical enters the eye, begin rinsing immediately with clean water or saline for at least 15 minutes, then seek emergency care right away.
- Eye injury from trauma, chemicals, or a foreign object
- New flashes of light or floating spots, especially with vision changes or after trauma
- White pupil seen in photos or in person
- New constant eye turn or sudden misalignment
- Bulging of one or both eyes
- Pupils of different sizes or pupils that do not react to light
- Extreme light sensitivity with tearing and discomfort, especially in infants
- Sudden eyelid swelling with fever or eye bulging
- Painful red eye with decreased vision
Eye Exams and Testing for Children
Comprehensive eye exams give a full picture of your child's visual health, well beyond what school or pediatric screenings can detect. Understanding how and when exams are done helps you plan ahead for your child's care.
Vision care begins with screenings at birth and regular well-child visits. Newborns receive a red reflex screening shortly after birth, and screenings continue throughout early childhood. These help identify children who need referral for a comprehensive eye exam.
We recommend a comprehensive exam for infants with risk factors between six and twelve months, and a universal comprehensive exam for all children between ages three and five. After starting school, exams every one to two years are appropriate, or more frequently for children who wear glasses, have a family history of eye conditions, or show any signs of vision difficulty.
- Premature birth or a history of retinopathy of prematurity
- Family history of childhood eye conditions such as amblyopia, strabismus, or high refractive error
- Developmental delays or neurological conditions
- Genetic syndromes associated with eye problems
- Diabetes, juvenile arthritis, or medications that can affect the eyes
- Previous eye injury or surgery
Vision screenings at schools or pediatrician offices are a helpful first step, but they are not a substitute for a comprehensive eye exam. Screenings typically test distance vision only and often miss farsightedness, focusing problems, eye coordination issues, and conditions affecting eye health. Many children pass screenings despite having significant vision problems.
A comprehensive exam conducted by an eye doctor evaluates all aspects of vision and eye health using specialized equipment. Passing a screening is encouraging, but it does not guarantee that everything is fine. Regular comprehensive exams are still recommended to catch what screenings cannot.
A comprehensive pediatric eye exam goes far beyond reading a letter chart. We evaluate how well the eyes work together, assess focusing abilities, and examine the health of the eye inside and out. The examination includes tests for refractive errors, eye alignment, depth perception, and color vision.
We use age-appropriate techniques to keep exams comfortable and engaging. Pupil dilation, using special eye drops, allows us to examine the internal structures of the eye thoroughly. The drops may sting briefly and can cause light sensitivity and blurry near vision for a few hours. Sunglasses or a hat can ease discomfort after the exam, and close reading tasks should be avoided until the drops wear off.
Testing very young children requires methods that do not depend on verbal responses. For infants, we observe how they track and follow objects, assess eye contact, and check pupil reactions to light. Specialized handheld instruments can measure refractive errors without any verbal feedback from the child.
For toddlers, we may use pictures, shapes, or matching games instead of letter charts. These child-friendly methods give us accurate information about visual acuity and eye function. Even very young children can have thorough, effective eye examinations with the right approach.
We use advanced diagnostic tools when needed based on your child's age, symptoms, exam findings, and risk factors. These are not routine tests for every visit but targeted tools to evaluate specific concerns or monitor known conditions.
Retinal imaging creates detailed pictures of the back of the eye to document and monitor eye health over time. Automated refraction devices provide quick estimates of focusing errors and can be especially helpful with young or uncooperative children, though they work alongside rather than replacing a full dilated refraction in most pediatric cases.
- Corneal topography to map the surface shape of the eye
- Optical coherence tomography (OCT) for detailed retinal imaging
- Visual evoked potential testing to assess the visual pathway to the brain
- Binocular vision testing to evaluate how well the eyes work as a team

Treatment Options for Children's Vision Problems
Most childhood vision conditions are treatable, especially when identified early. Our team works with you and your child to find the right approach for their specific needs and age.
Glasses remain the most common and effective treatment for refractive errors in children. Modern frames are durable, comfortable, and available in styles children enjoy wearing, which makes consistent use much easier. We help families choose frames that fit well and hold up to active play.
Contact lenses may be appropriate for older children and teenagers who can handle the responsibility of proper care. Some children as young as eight or nine successfully wear contacts, particularly for sports. We evaluate maturity and hygiene readiness when determining whether a child is ready for contact lens wear.
- Always wash hands thoroughly before handling lenses
- Never sleep in contact lenses unless specifically prescribed for overnight wear
- Remove lenses before swimming, showering, or any water exposure
- Follow the recommended replacement schedule for your lens type
- Use fresh solution as directed and never reuse old solution
- Stop wearing lenses immediately and contact us if you notice pain, redness, light sensitivity, or discharge
Patching the stronger eye forces the brain to rely on the weaker eye, gradually strengthening the visual pathways and improving vision over time. Treatment typically involves wearing the patch for several hours each day while doing visually engaging activities like reading, drawing, or puzzles. The schedule and duration depend on the severity of amblyopia and your child's age.
Progress develops gradually over weeks to months, and consistency is essential to good outcomes. We monitor your child closely and adjust the patching schedule as their vision improves. Combining glasses with patching often produces the best results when both are needed.
Vision therapy is a structured program of visual activities designed to improve eye coordination, focusing skills, and visual processing. This treatment is evidence-based for certain binocular vision disorders, such as convergence insufficiency, some types of accommodative dysfunction, and selected eye movement deficits. Vision therapy is not a replacement for glasses and is not a primary treatment for dyslexia or learning disabilities, which require educational and developmental interventions.
Sessions are supervised by our team, with exercises often continued at home between visits. We carefully evaluate each child to determine whether they are a good candidate. For appropriate patients, therapy can reduce eye strain, improve reading comfort, and support visual performance in school and sports.
Myopia control refers to treatments that aim to slow the progression of nearsightedness in children. These approaches reduce how quickly the prescription increases on average, though results vary. Myopia control does not cure or reverse nearsightedness, and glasses or contacts are still needed for clear distance vision. The goal is to lower the rate of prescription change and reduce the long-term risks that come with high levels of myopia.
We consider myopia control for children with progressive nearsightedness, especially those with a family history of high myopia or whose condition starts at a young age. Available options include specialized multifocal soft contact lenses, orthokeratology lenses worn overnight to reshape the cornea, low-dose atropine eye drops, and eyeglass lenses with a peripheral defocus design.
- Daytime multifocal contact lenses worn like regular contacts
- Orthokeratology lenses worn overnight and removed in the morning
- Low-dose atropine drops applied nightly to slow eye growth
- Specialized eyeglass lenses designed to reduce myopia progression
All myopia control treatments require regular follow-up to measure refraction, monitor eye health, and adjust the approach as needed. Contact lens options carry a risk of eye infection, and orthokeratology in particular requires strict hygiene, no water exposure to lenses, and prompt attention for any pain, redness, light sensitivity, or discharge.
Surgery may be recommended when a condition does not respond adequately to other treatments. Strabismus surgery adjusts the eye muscles to improve alignment and restore coordinated eye movement. These procedures are generally safe and effective, though some children may need more than one surgery to achieve the best result.
Other surgical interventions address structural problems such as blocked tear ducts, drooping eyelids that obstruct vision, or congenital cataracts. We thoroughly discuss all surgical options, including benefits, risks, and alternatives, so you can make a fully informed decision about your child's care.
Growing children often need prescription changes, and conditions like amblyopia require close monitoring throughout treatment. Regular follow-up visits allow us to track how well treatments are working and make adjustments as needed. Visit frequency is determined by your child's specific condition and treatment plan.
Between appointments, contact us if you notice new symptoms, if glasses break, or if your child is resisting treatment. Staying in touch helps us address concerns quickly and keep your child's vision on the right track.
Supporting Your Child's Eye Health at Home
Healthy vision habits at home complement professional care and can help protect your child's eyesight as they grow. Small daily changes can make a meaningful difference over time.
Prolonged near work and reduced outdoor time, including sustained screen use and reading, are associated with digital eye strain and increased myopia risk. The 20-20-20 rule offers a simple way to reduce eye fatigue. Every 20 minutes, have your child look at something at least 20 feet away for at least 20 seconds.
Limit recreational screen time according to age-appropriate guidelines and encourage regular breaks during homework or necessary computer use. Position screens at a comfortable distance and height with good lighting that minimizes glare. Building these habits now helps protect vision in the years ahead.
Research shows that children who spend more time outdoors have a lower risk of developing myopia or experience slower progression if they are already nearsighted. Natural light and the habit of focusing on distant objects during outdoor play may help protect against nearsightedness. Aiming for at least 90 to 120 minutes of outdoor time daily, when possible, is a reasonable goal.
Even quiet outdoor activities appear to offer protective benefits compared to indoor tasks. When spending extended time in bright sunlight, protect your child's eyes with a brimmed hat and sunglasses that provide UV protection.
Eye injuries are common in children but are often preventable with the right protective eyewear. Sports such as basketball, baseball, hockey, and racquet sports pose significant eye injury risks. Impact-resistant goggles or face shields designed for specific sports can prevent serious harm.
- Use polycarbonate lenses in sports eyewear for maximum impact resistance
- Ensure protective goggles fit properly and stay secure during activity
- Verify that prescription sports glasses meet established safety standards
- Wear appropriate protection during science experiments or workshop activities
- Supervise young children around toys with small projectile parts
A balanced diet rich in key nutrients supports healthy eye development. Omega-3 fatty acids found in fish support retinal health, while colorful fruits and vegetables provide antioxidants that protect eye tissues. Vitamin A is essential for good vision, particularly in low-light conditions.
Encourage a variety of nutritious foods rather than relying on supplements alone. Leafy greens, carrots, sweet potatoes, citrus fruits, nuts, and fish all contribute to eye health. At home, ensure good lighting for reading and homework, teach children to hold reading materials about 14 to 16 inches from their eyes, and encourage proper posture during screen time to reduce neck and eye strain.
Frequently Asked Questions
These answers address questions that go beyond what is covered in detail above, offering guidance to help you make confident decisions about your child's eye care.
Some mild farsightedness does resolve naturally as the eyes grow, and this is why many young children with low hyperopia have no symptoms and need no treatment. However, conditions like strabismus and amblyopia rarely resolve on their own and require active treatment to prevent permanent vision loss. Waiting to see if a problem improves on its own can reduce the window of time when treatment is most effective, so professional evaluation is always the right first step.
Current evidence does not support the idea that screens cause permanent structural damage to the eyes. However, excessive near work, including prolonged screen use, is associated with temporary eye strain, dry eyes, and fatigue. There is also growing evidence linking heavy near work and reduced outdoor time to an increased risk of myopia development and progression. The key is balance: structured breaks, outdoor time, and good viewing habits allow children to benefit from technology without unnecessary strain.
By two to three months, most babies should make eye contact and follow faces or moving objects with their eyes. Between four and six months, infants typically begin reaching for objects they see. If your baby shows little interest in faces or toys, if one or both eyes wander constantly, or if anything about the eye's appearance seems unusual, schedule an evaluation rather than waiting for the next routine checkup. Early exams are straightforward and provide important reassurance or catch problems while they are most treatable.
This is a common concern, but wearing properly prescribed glasses does not weaken the eyes or create dependence. If your child's prescription increases over time, that reflects natural eye growth during childhood, not any harm caused by wearing glasses. In fact, going without needed glasses can place unnecessary strain on the visual system and, in some cases, interfere with normal visual development. Glasses support clear, comfortable vision and help the eyes develop properly.
These terms are often confused but describe different conditions. Strabismus refers to a visible misalignment of the eyes where one or both eyes point in the wrong direction. Amblyopia, or lazy eye, refers to reduced vision in one eye caused by the brain favoring the other, and it is not always visible from the outside. Strabismus is a common cause of amblyopia, but amblyopia can also result from a large prescription difference between the eyes or from anything that blocks vision early in life. Both conditions benefit from early diagnosis and treatment.
Myopia control is worth discussing if your child's nearsightedness is progressing steadily, if they were diagnosed at a young age, or if there is a family history of high myopia. The concern is not just about stronger prescriptions but about the increased risk of retinal problems and other complications that come with high levels of myopia over a lifetime. If your child's myopia is stable and mild, monitoring may be all that is needed. Our team can review your child's prescription history, examine their eyes, and help you decide whether a myopia control approach makes sense for their situation.

Schedule a Pediatric Eye Exam at Rhode Island Eye Institute
Your child's vision shapes how they learn, move, and connect with the world around them. At Rhode Island Eye Institute, our experienced pediatric eye care team brings compassion and advanced diagnostic tools to every visit, giving your child the thorough, personalized care they deserve. Whether you have a specific concern or simply want to stay on top of your child's visual health, we are here to help at every stage of their development.